Can trigger point injections help sciatica-like pain from piriformis syndrome?
Trigger point injections may help some people with sciatica-like pain when the piriformis muscle contributes to symptoms. They do not treat every cause of sciatica.
Pain traveling from the buttock into the thigh or leg may come from a lumbar disc, spinal stenosis, nerve-root irritation, the hip, sacroiliac joint, another deep-gluteal structure, or referred muscle pain. A normal lumbar MRI does not prove that the piriformis is responsible.
When examination findings support piriformis involvement and conservative care has not helped enough, a targeted injection may have diagnostic and therapeutic value.
What Is Piriformis Syndrome?
The piriformis is a small muscle deep in the buttock that helps with hip rotation and stability. The sciatic nerve travels close to it.
Piriformis syndrome is used when the muscle is suspected of irritating or contributing to symptoms involving the nearby sciatic nerve. Possible factors include spasm, overuse, trauma, scarring, anatomical variation, or altered hip mechanics.
Diagnosis can be difficult because no single test confirms every case. Common clues include buttock pain, pain worsened by sitting, deep gluteal tenderness, and pain during maneuvers that tension the piriformis.
What Is Deep Gluteal Syndrome?

Deep gluteal syndrome is a broader term for non-spinal sciatic-nerve irritation in the deep buttock. The piriformis may be involved, but nearby muscles, fibrous bands, the hamstring origin, or other pelvic structures may also contribute.
Piriformis Syndrome vs. Lumbar Sciatica
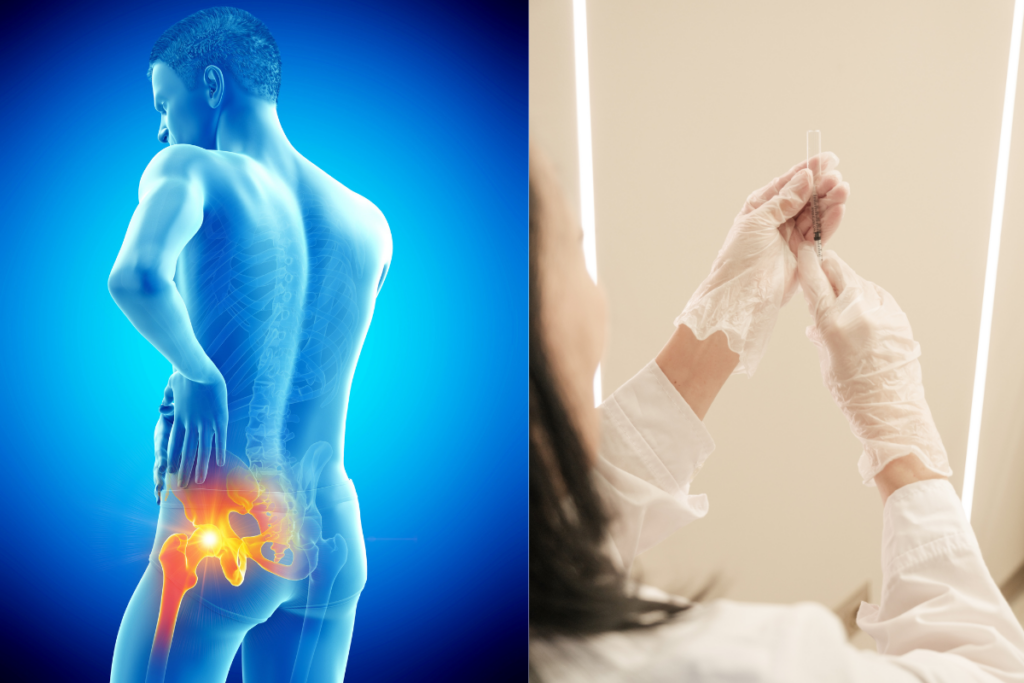
Piriformis-related pain often centers in the deep buttock and may worsen with sitting or hip movement. Lumbar nerve-root sciatica is more likely to involve lower-back symptoms, radiating leg pain, neurological changes, or pain affected by spinal movement.
Common Symptoms and Red Flags
Possible symptoms include deep buttock pain, pain with prolonged sitting or driving, hip-rotation pain, tenderness, pain down the back of the thigh, tingling, or reduced walking tolerance.
Seek prompt medical assessment for progressive weakness, foot drop, saddle numbness, bowel or bladder loss, fever, major trauma, or worsening difficulty walking.
How Is It Diagnosed?
Evaluation usually includes medical history and physical examination. A clinician may review pain location, back involvement, sitting tolerance, numbness or weakness, injury history, hip movement, and prior treatment.
The examination may assess strength, reflexes, sensation, hip and lumbar movement, neural-tension tests, and maneuvers such as FAIR or seated piriformis testing. No individual test is definitive.
Is Imaging Always Needed?
No.
Imaging is more relevant when symptoms persist, neurological deficits worsen, intervention is being considered, or red flags suggest a serious condition.
What Is a Piriformis Trigger Point Injection?
A piriformis injection places a needle into or around the piriformis muscle for diagnostic or therapeutic purposes.
Depending on the case, the injectate may include local anesthetic, saline, local anesthetic with corticosteroid, or botulinum toxin in selected specialist cases.
A deep piriformis injection is different from an epidural injection, nerve-root block, hip injection, dry needling, or acupuncture.
How Might It Help?
A local-anesthetic injection may temporarily reduce pain from the targeted muscle. Short-term relief can support—but does not prove—the diagnosis.
It may also reduce local pain or muscle guarding and make rehabilitation easier. It does not repair a disc, treat spinal stenosis, or prevent recurrence.
What Does the Evidence Show?
A randomized trial of 50 patients with suspected piriformis syndrome compared ultrasound-guided lidocaine alone with lidocaine plus betamethasone. Both groups improved, with no significant difference between them through three months.
Is Ultrasound Guidance Important?
The piriformis lies deep near the sciatic nerve and blood vessels. Ultrasound or other imaging can help identify the target and nearby structures.
Who May Be Considered?
An injection may be considered when buttock pain is prominent, sitting or hip movement worsens symptoms, examination supports piriformis involvement, spinal and hip causes have been considered, conservative treatment has not helped enough, and no urgent neurological warning signs are present.
It should not be recommended only because a tender spot was found or an MRI was normal.
Who Should Avoid or Postpone Treatment?
Treatment may need to be postponed or modified for infection, fever, bleeding risk, certain blood-thinning medications, drug allergy, uncontrolled diabetes when steroid is considered, pregnancy without review, progressive neurological deficits, suspected cauda equina syndrome, or an unclear diagnosis.
Do not stop blood thinners on your own.
What Happens During the Procedure?
The clinician reviews symptoms, medications, allergies, imaging, neurological findings, risks, and alternatives.
The patient is positioned safely, the skin is cleaned, and a sterile needle is guided toward the piriformis. A small amount of medication is injected.
You may feel pressure, a pinch, muscle twitching, or brief reproduction of familiar pain. Report sudden electrical pain or unusual symptoms immediately.
Risks and Side Effects
Temporary effects may include soreness, bruising, minor bleeding, numbness, weakness, dizziness, or a short pain flare.
Less common risks include infection, hematoma, allergic reaction, nerve or blood-vessel injury, steroid-related tissue changes, elevated blood sugar, persistent pain, or no benefit.
Seek urgent care for trouble breathing, facial or throat swelling, sudden severe weakness, saddle numbness, or loss of bowel or bladder control.
What to Expect Afterward
Some people notice relief quickly because of the local anesthetic. Others improve over several days, experience only temporary benefit, or do not improve.
Track pain, sitting tolerance, walking, leg symptoms, and side effects. Immediate numbness should not be mistaken for permanent improvement.
Why Rehabilitation Still Matters
An injection may reduce pain but does not correct every contributing factor.
Rehabilitation may include walking, hip and gluteal strengthening, core control, mobility work, sitting changes, and return-to-activity progression.
Aggressive stretching may worsen symptoms when the sciatic nerve is irritable. Stop if stretching causes sharp pain, burning, numbness, tingling, or symptoms spreading down the leg.
Complementary Options
Depending on the diagnosis, treatment may also include medical massage, osteopathic manipulative treatment, rehabilitation, medication, or specialist referral.
These approaches should not replace urgent evaluation when neurological red flags are present.
How Long Does Relief Last?
There is no universal timeline. Relief may last hours, days, weeks, or longer in selected patients.
Duration depends on diagnosis, injection placement, medication, rehabilitation, activity demands, and coexisting spinal or hip problems.
There is no evidence-based rule that every patient needs a preset series of injections.
How Long Does Relief Last?
There is no universal timeline. Relief may last hours, days, weeks, or longer in selected patients.
Duration depends on diagnosis, injection placement, medication, rehabilitation, activity demands, and coexisting spinal or hip problems.
There is no evidence-based rule that every patient needs a preset series of injections.
Insurance and Circle Wellness
Circle Wellness states that it accepts NYSHIP for direct insurance billing. Trigger point injections may be covered when medically necessary, but coverage depends on diagnosis, documentation, utilization review, provider status, and the final claim.
Circle Wellness offers physician- and physician-assistant-administered trigger point services in Melville.
FAQs

Can trigger point injections cure piriformis syndrome?
No. They may reduce pain in selected patients, but recurrence is possible.
Can they cure sciatica?
No. They do not repair a herniated disc or decompress a spinal nerve root.
Does a normal MRI prove piriformis syndrome?
No. Diagnosis still requires clinical correlation.
Are piriformis injections the same as epidural injections?
No. A piriformis injection targets muscle; an epidural targets the spinal epidural space.
Is steroid always necessary?
No. One randomized trial found no significant advantage from adding corticosteroid to lidocaine.
Can massage help?
Medical massage may help surrounding muscular tension but should not replace evaluation of progressive weakness, severe numbness, or other neurological warning signs.
When should I seek emergency care?
Seek urgent care for bowel or bladder loss, saddle numbness, progressive weakness, foot drop, severe bilateral symptoms, fever with severe back pain, or major trauma.
Key takeaways
- Sciatica is a symptom pattern, not one diagnosis.
- Piriformis syndrome is one possible cause of buttock and leg pain.
- Trigger point injections target muscle; they do not repair a disc or decompress a spinal nerve root.
- Evidence suggests possible pain relief in selected patients, but studies are limited.
- Progressive weakness, foot drop, bowel or bladder changes, saddle numbness, fever, or major trauma require prompt evaluation.
- Relief may be temporary, incomplete, or absent.
- Rehabilitation remains important.
Final Takeaway
Trigger point injections may help selected patients when piriformis or deep-gluteal muscular pain contributes to sciatica-like symptoms. They are not a universal sciatica treatment.
A responsible plan should identify the pain source, screen for neurological red flags, evaluate the spine and hip, explain the injection, set realistic expectations, measure response, and combine symptom relief with rehabilitation when appropriate.
The goal is to determine whether the piriformis meaningfully contributes to symptoms and whether an injection offers reasonable benefit compared with the risks and alternatives.